
Nutritional Gaps Among American Children and Adolescents: Insights From a 2026 NHANES Analysis
A recent analysis based on the National Health and Nutrition Examination Survey (NHANES; 2001-2020) shows inadequate intake of certain key nutrients among children and adolescents aged 1 to 18 years in the United States.1 The important findings highlight the need for age- and gender-specific strategies to address nutritional gaps.1
Critical nutritional gaps are observed across childhood
Children and adolescents aged 1-13 years in the United States have inadequate intake of 5 key nutrients: docosahexaenoic acid (DHA), eicosapentaenoic acid (EPA), dietary fiber, vitamin D, and vitamin E.1- DHA and EPA:
- Low intake of DHA and EPA was observed across all ages and genders.1 While intake increased across age groups, combined DHA + EPA intake was below US reference values in over 96% of children in all age and gender groups.1-3
- Dietary fiber:
- Dietary fiber was under-consumed by all age groups (less than 3% of children and adolescents had adequate intake), and intake density (grams per 1,000 kcal per day) decreased with age.1
- Vitamin D:
- Over 60% of children aged 1 to 8 years reported inadequate vitamin D intake; this inadequacy increased with age, with more than 75% of those aged 9 to 13 years under-consuming.1
- Vitamin E:
- For vitamin E, although usual vitamin E intake increased across age groups, intakes did not keep pace with the increased needs.1 More than 35% of children aged 1 to 8 years and over 65% of those aged 9 to 13 years reported inadequate vitamin E intake.1
These findings are supported by a 2021 NHANES analysis of children aged 1 to 6 years, which showed iron deficiency and inadequate intakes of fiber, calcium, choline, potassium, DHA, vitamin D, and vitamin E.4
Nutritional gaps worsened with age for several nutrients including dietary fiber, calcium, magnesium, phosphorus, potassium, and vitamins A, D, and E.1 Furthermore, inadequate intake of certain nutrients—particularly calcium, phosphorus, zinc, folate, and iron—was more pronounced among the older females.1
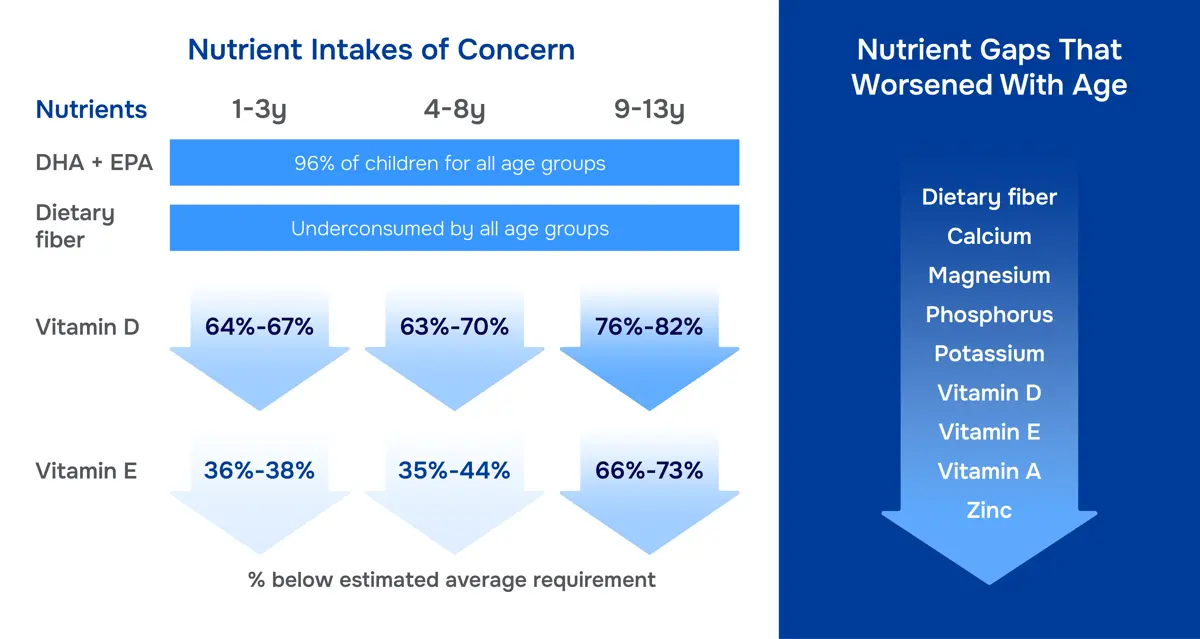
Figure 1. Summary of nutrient intakes of concern from a 2026 NHANES analysis.a,1
DHA, docosahexaenoic acid; EPA, eicosapentaenoic acid; NHANES, National Health and Nutrition Examination Survey.
aAcceptable macronutrient distribution range data were not available for DHA + EPA. The proportions represented reflect the proportions who consumed below 70 mg/d for those aged 1 to 3 years, 90 mg/d for those aged 4 to 8 years, 100 mg/d for 9- to 13-year-old females, and 120 mg/d for 9- to 13-year-old males.1
For some nutrients, dietary intake may not fully explain deficiency risk
Biomarker data highlight that dietary intake is not always predictive of nutritional status.1 For example, while inadequate intake of vitamin A and vitamin E was observed, a very small percentage of children had a low serum level of retinol or vitamin E, respectively.1
Conversely, intake sometimes underestimated nutrient deficiency.1 Among females aged 14 to 18 years, 11.1% and 14.7% had intake below the estimated average requirement for iron and folate, respectively.1 Deficiency and insufficiency prevalence was higher, however, when based on biomarkers: 29.9% exhibited low serum ferritin and 19.7% showed a low folate concentration in red blood cells.1
Overall, the deficiency results reported in this study are also consistent with a 2022 study published in The Lancet that identified micronutrient deficiencies in over half of preschool-aged children and two-thirds of nonpregnant women of reproductive age worldwide; both groups are more vulnerable to micronutrient deficits due to high requirements.5
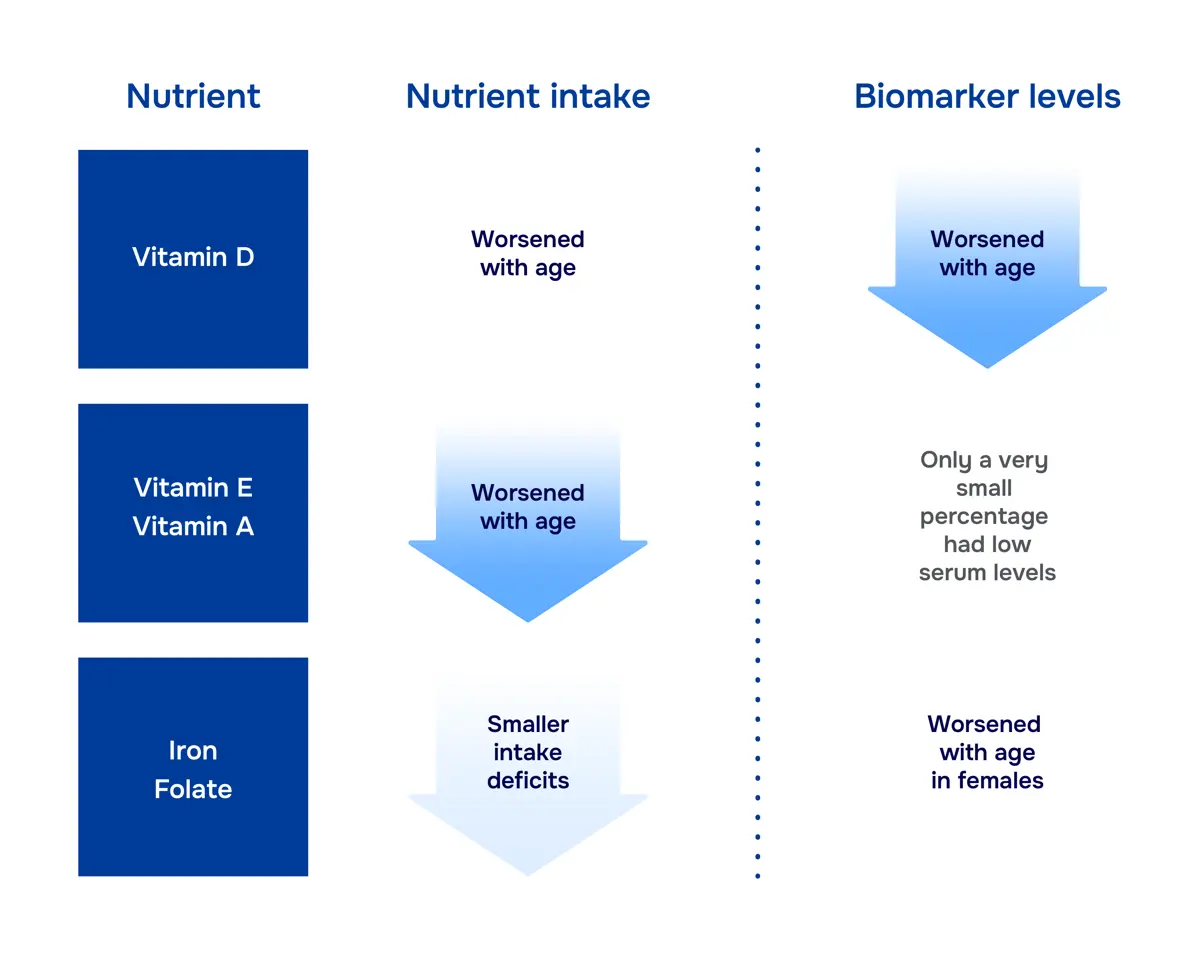
Figure 2. Summary of nutrient intake versus biomarker levels among children and adolescents aged 1 to 18 years, based on an analysis of NHANES data (2001-2020).1
NHANES, National Health and Nutrition Examination Survey.
Summary
These findings have important implications for future research and for future iterations of dietary guidelines and public health policies.1 This analysis also emphasizes the need for targeted age- and gender-specific approaches to addressing nutritional gaps among children and adolescents in the United States, and for further research to refine nutrition requirements.1
The full study and results can be accessed at https://doi.org/10.1016/j.tjnut.2026.101377.
- Bailey ADL, Miketinas DC, London HE, Houslay T, Bender TM, Patterson AC. Usual nutrient intake adequacy and nutritional status of United States children and adolescents: National Health and Nutrition Examination Survey 2001–March 2020. J Nutr. 2026;156(3):101377. doi:10.1016/j.tjnut.2026.101377
- Institute of Medicine. Dietary reference intake for energy, carbohydrate, fiber, fat, fatty acids, cholesterol, protein, and amino acids. The National Academies Press; 2005. doi.org/10.17226/10490
- European Food Safety Authority (EFSA). Dietary reference values for nutrients summary report. Approved December 4, 2017. Accessed July 24, 2026. https://www.efsa.europa.eu/sites/default/files/2017_09_DRVs_summary_report.pdf
- Bailey ADL, Fulgoni VL III, Shah N, et al. Nutrient intake adequacy from food and beverage intake of US children aged 1-6 years from NHANES 2001-2016. Nutrients. 2021;13(3):827. doi:10.3390/nu13030827
- Stevens GA, Beal T, Mbuya MNN, Luo H, Neufeld LM; Global Macronutrient Deficiencies Research Group. Micronutrient deficiencies among preschool-aged children and women of reproductive age worldwide: a pooled analysis of individual-level data from population-representative surveys. Lancet Glob Health. 2022;10(11):e1590-e1599. doi:10.1016/S2214-109X(22)00367-9



